 EndoTODAY 내시경 교실
Beginner | ESA | Schedule | OPD
Seminars | Atlas | Recent | Links
 [Gastric cancer 471]
001 | 101 | 201 | 301 | 401 | 501 | 601 | 701 | 801 | 901 | 1000
오래 전 total gastrectomy를 받은 환자의 추적내시경을 하면서 예전 사진을 찾아보았습니다.
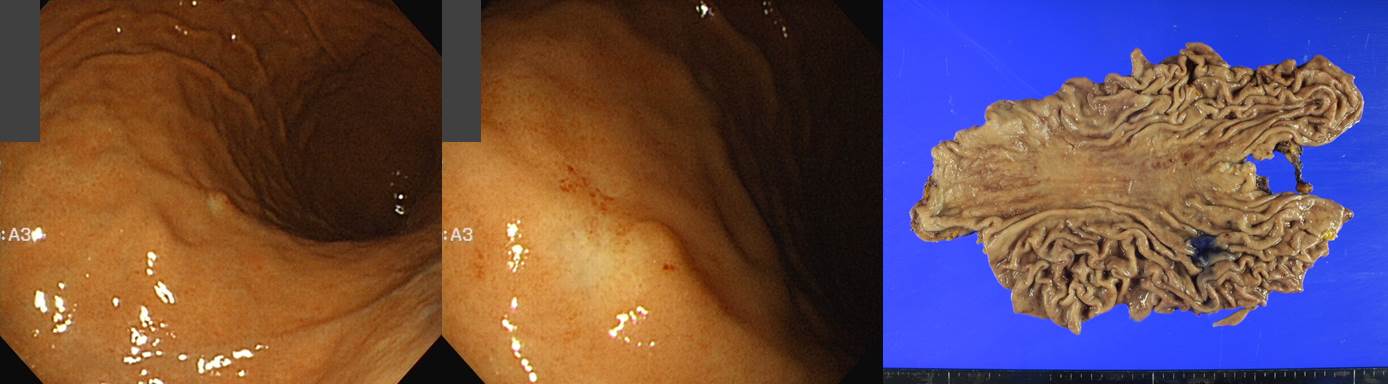
Stomach, total gastrectomy:
Early gastric carcinoma
1. Location : middle third, Center at high body and greater curvature
2. Gross type : EGC type IIb
3. Histologic type : signet-ring cell carcinoma
4. Histologic type by Lauren : diffuse
5. Size : 1.0x0.4 cm
6. Depth of invasion : invades mucosa (lamina propria) (pT1a)
7. Resection margin: free from carcinoma, safety margin: proximal 2 cm, distal 13 cm
8. Lymph node metastasis : no metastasis in 49 regional lymph nodes (pN0) (0/49: "1", 0/2; "2", 0/5; "4sb", 0/0; "5", 0/0; "6", 0/5; "7", 0/0; "8a", 0/2; "9", 0/1; "11p", 0/3; "12a", 0/5; "LN3,5", 0/11; "LN4,6", 0/15)
9. Lymphatic invasion : not identified
10. Venous invasion : not identified
11. Perineural invasion : not identified
지금도 그렇고 이 환자가 수술받으신 10년 전에는 더욱 그렇습니다. Total gastrectomy가 정답입니다. 그러나 아쉬움이 남습니다. 우리가 너무 적극적으로 치료했던 것은 아닐까? 내시경 치료의 적응증을 넓혀볼 것인가? Wedge resection은 정말 안 되는 것인가? 림프절 곽청술이 지나쳤던 것은 아닐까? 추적내시경은 의미가 있을까? (Lee SY. EJSO 2005) 답도 없는 고민은 계속되고 이 밤은 깊어갑니다.
© 일원내시경교실 바른내시경연구소 이준행. EndoTODAY Endoscopy Learning Center. Lee Jun Haeng.