EndoTODAY 내시경 교실
Beginner | ESA | Schedule | OPD
Seminars | Atlas | Recent | Links
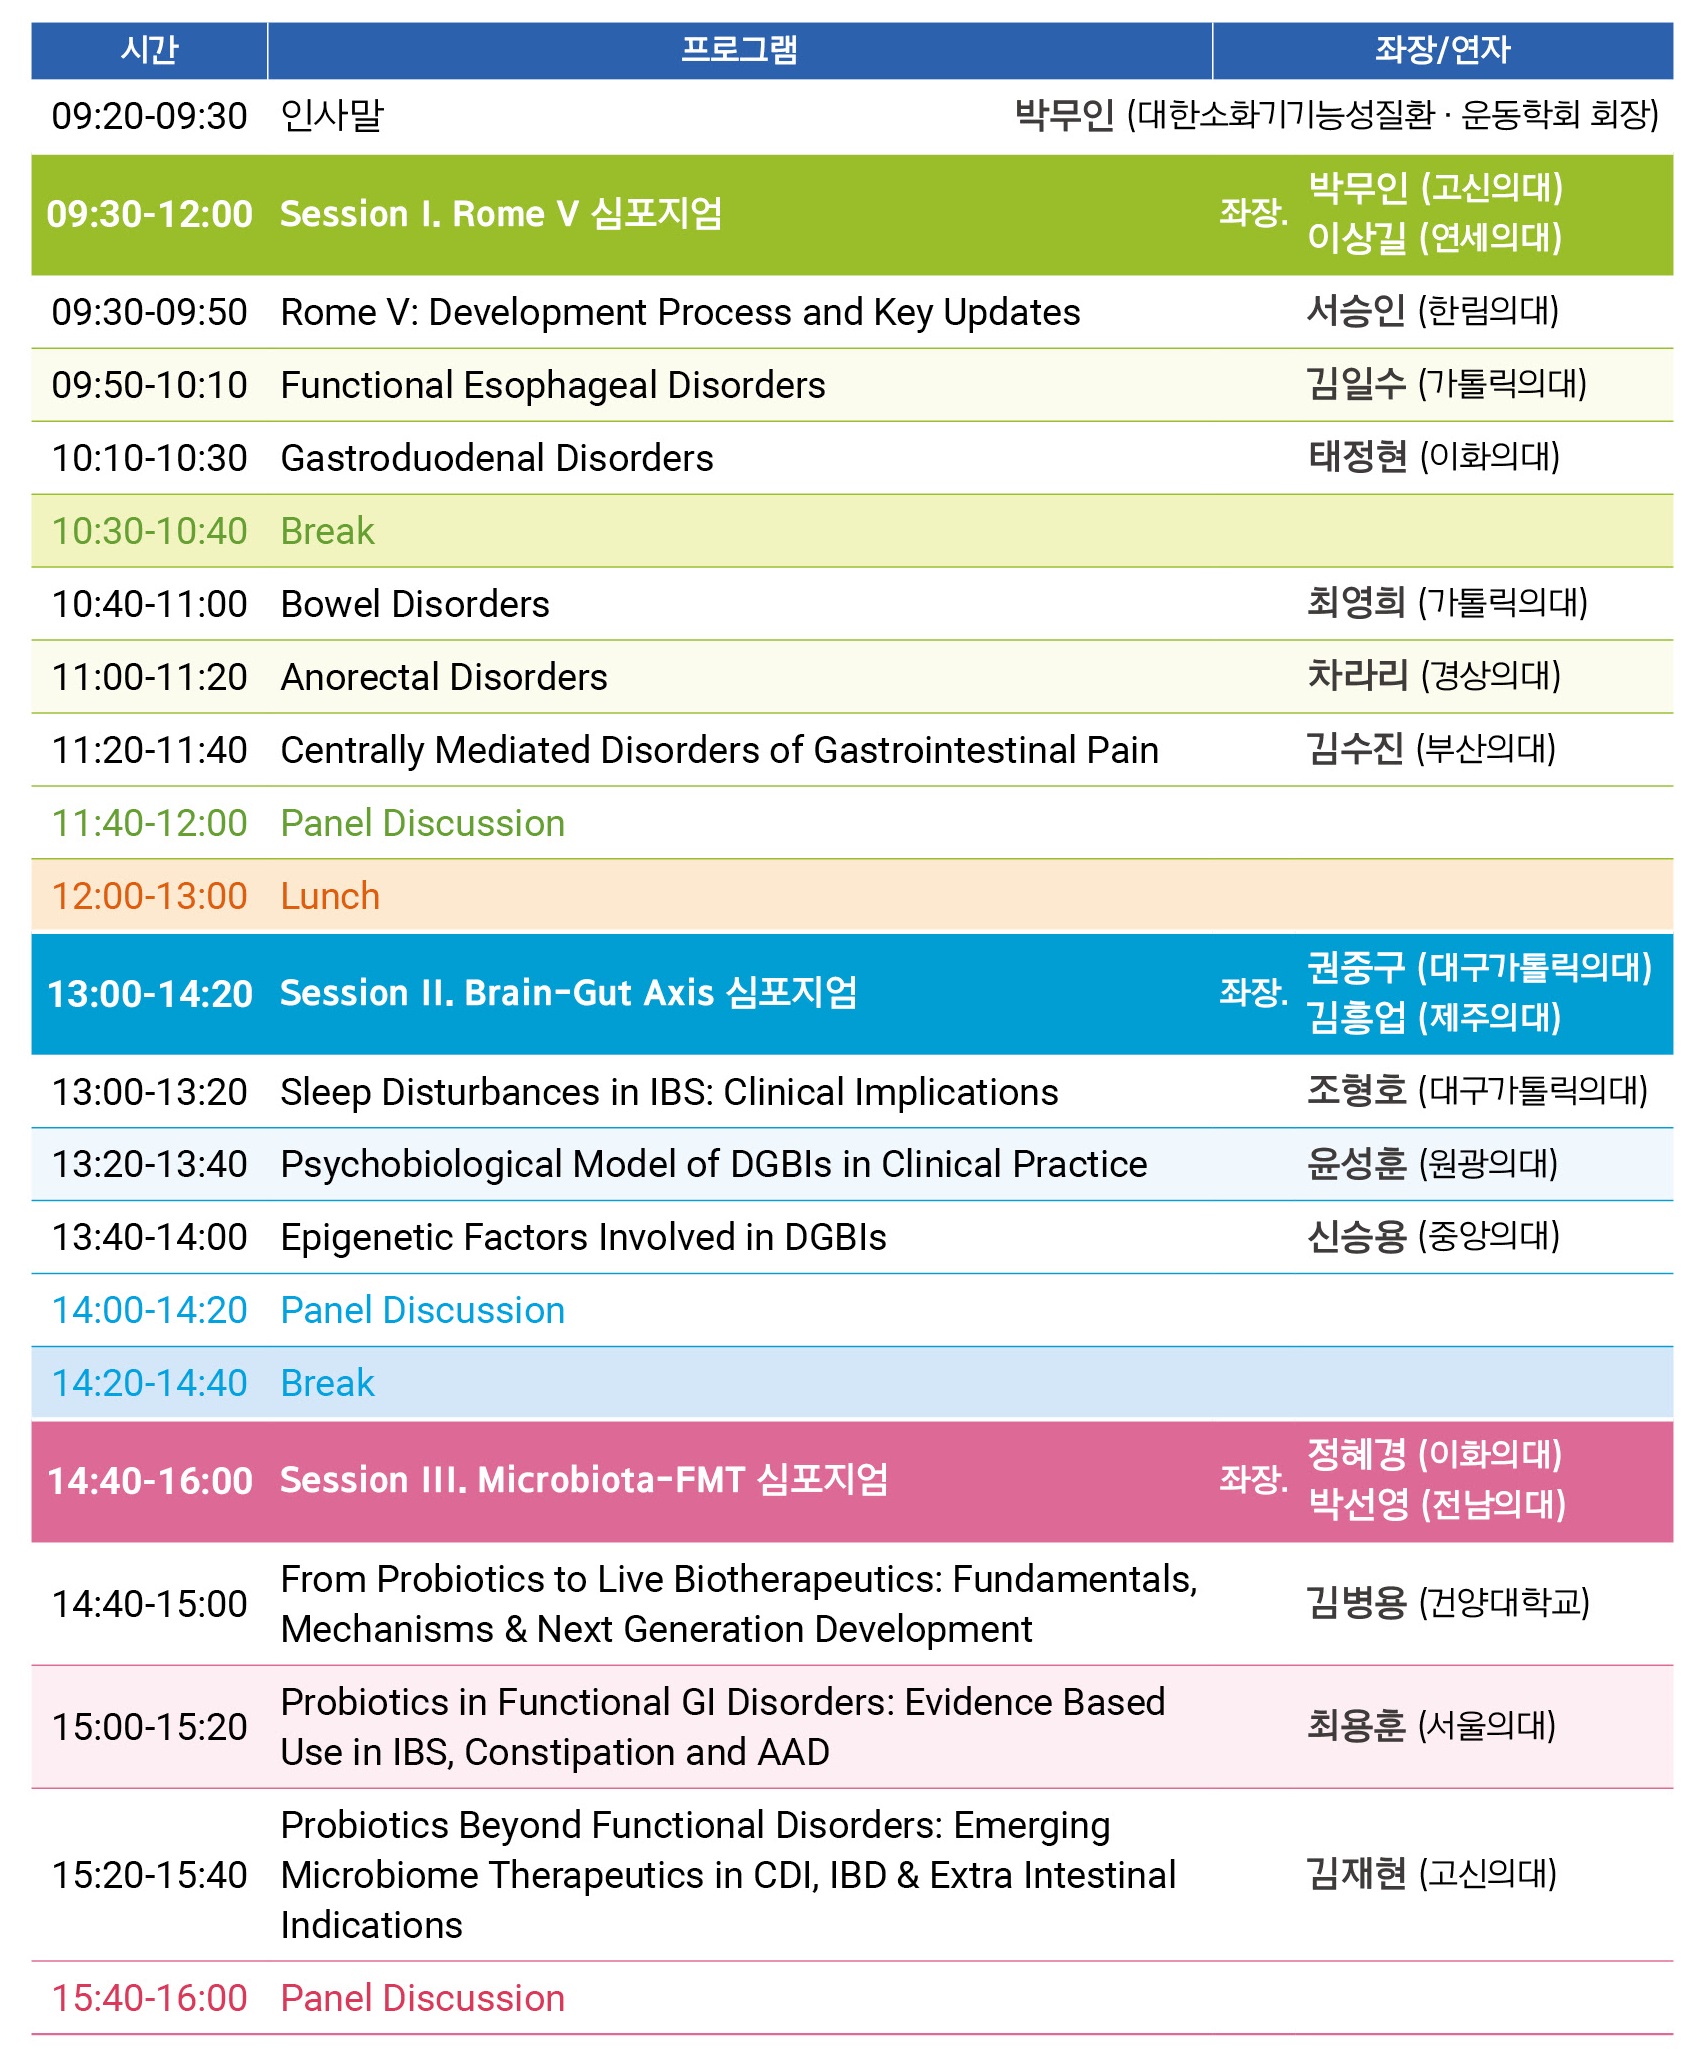
 [Rome 5 symposium (2026)] - 終
 1. Introduction to Rome 5
7년에 걸쳐, 27국의 144명의 전문가가 만들었다. Rome 4가 restrictive하다면 Rome 5는 permissive하고 환자중심이다.
Rome 3부터 근거 중심으로, Rome 4-5부터 지역간, 인종간 차이까지 반영하였다.
가장 중요한 변화 5가지
Rome criteria를 임상에 적용할 때의 한계점
동양인은 상부 증상과 하부 증상이 깔끔하게 구분되지 않고 식사와 연결이 된다.
Rome 5는 연구중심이 아니라 임상에서 사용할 있도록 만들었다. 기간도 많은 경우에 6개월에서 8주로 단축하였다. Rome science into everyday practice.
Case-based diagnostic algorithm and multidimensioal clinical profiles for common DGBI using rome 5 criteria Am J Gastroenterol 2026
2. 상부
[식도]
GERD (Lyon 2)와 motility 질환(Chicago 4)을 배제한다.
A2. Funtional heartburn: Avoid anti-reflux surgery
A3. Reflux hypersensitivity: regurgitation과 belching은 포함되지 않는다.
A4. Globus: No gastric inlet patch on endoscopy. (Under the Rome V consensus criteria, the diagnostic and therapeutic approach to a gastric inlet patch (cervical inlet patch) in patients presenting with globus sensation has been substantially de-emphasized. While previous guidelines were highly permissive toward treating and ablating these patches, Rome V updates advocate for a much more conservative, non-procedural approach.) Stop a PPI that is not working
A5. Functional dysphagia: Empiric bougie 50-54 Fr; 68-85% respond. Avoid balloon dilatation at the EGJ
[위]
기능성 소화불량증으로 부르지 말고 EPS와 PDS로 부르기를 권유하였다. EPS와 PDS의 구분이 달라졌다. Rome 4에서는 증상이 통증인지 포만감인지에 따라 나누었는데 Rome 5에서는 식사와의 연관성을 중요시하였다. 식사에 의해 (meal-related) 유발되는 명치 통증은 PDS이다.
Meal-related EPS (환자 비율 40%), meal-unrelated EPS (환자 비율 60%)로 구분하였다. 잠정 기준: 50%
PDS 진단 algorithm 시작: Helicobacter 감염상태는 반드시 확인한다.
구역 또는 구토가 주된 증상인 경우 PDS가 아니다. CNVS이나 gastroparesis로 진단해야 한다.
3. 하부
[IBS]
배제진단이 아니다. 기준이 충죽되어야 한다. 경고 증후로 기질질환을 예측하는 것은 제한적이다.
"not continous" and "not only menses-related"
아형 분류는 BSFS로 나눈다.
Functional constipation이 chronic constipation으로 이름이 변경되었다. 그런데 functional diarrhea는 이름이 유지되었다. (이유는 무엇일까?)
Colonoscopy: consider if fecal calprotectin abnormal or suspected microscopic colitis (female, age >=50 years, co-existing autoimmune disease, nocturnal or severe watery diarrhea, duation of diarrhea < 12months, weight loss, or use of potential precipitating drugs (NSAIDs or PPIs))
[Anorectal]
Proctalgia Fugax - 항문직장 부위의 갑작스럽고 심한 통증이 수 초 - 수 분간 지속되다 완전히 소실된다. 대부분 연 5회 미만으로 드물게 발생한다.
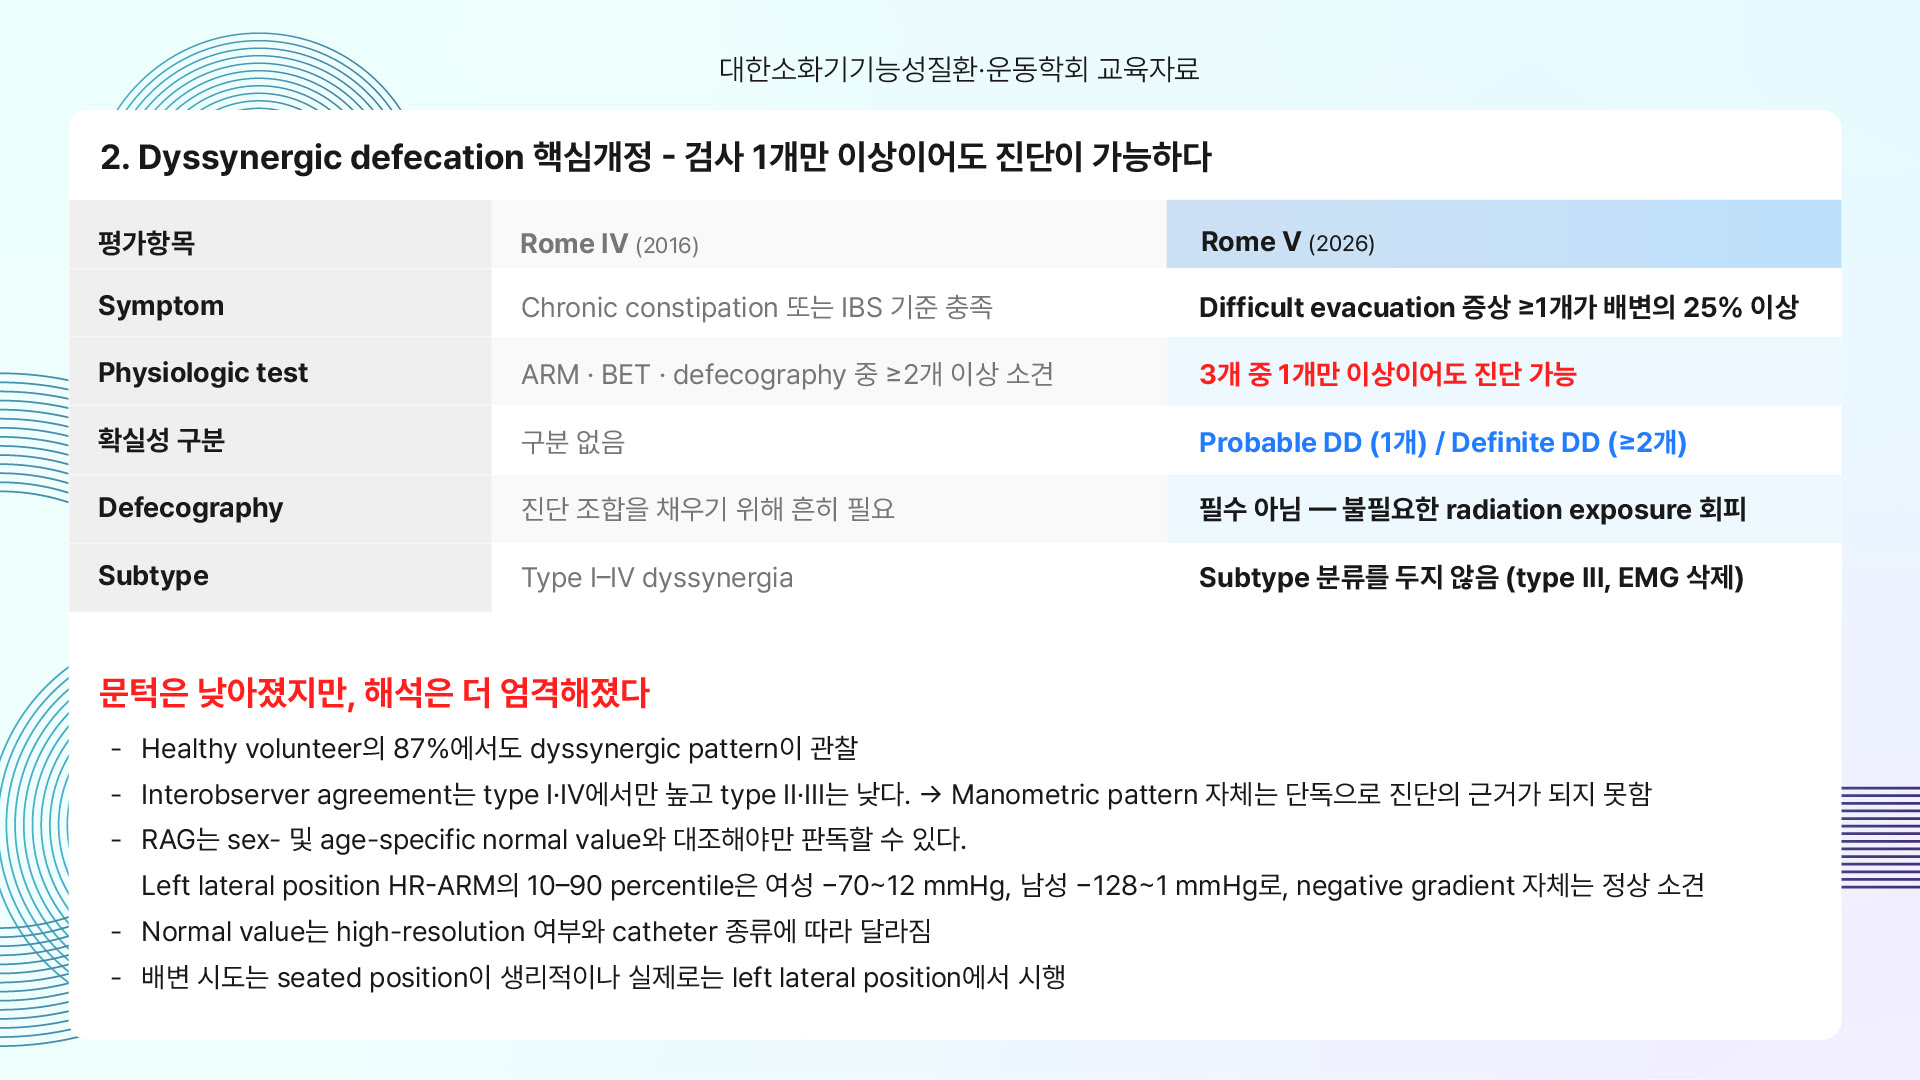
Functional defection disorder를 dyssynergic defecation으로 이름을 바꿨다.
[Centrally mediated disorders of gastrointestinal pain]
| Feature | IBS | CAPS (chronic abdominal pain syndrome) |
| Pain | intermittent/recurrent | Continuous |
| Relation to defecation | Characteristic | None (A) or variable (B) |
| Bowel habit change | Central feature | Not required |
| Paripheral factors | Important (diet, infection, mucosa) | Less dominant |
| Central pain processing | Important | Dominant |
| Functional impairment | Variable | Usually prominent |
[2026-9-30] 운동학회 교육자료 - anorectal disorders
[References]
1) FD Functional dyspepsia
© 일원내시경교실 바른내시경연구소 이준행. EndoTODAY Endoscopy Learning Center. Jun Haeng Lee (since 1999-8-23) color: R52G95B83